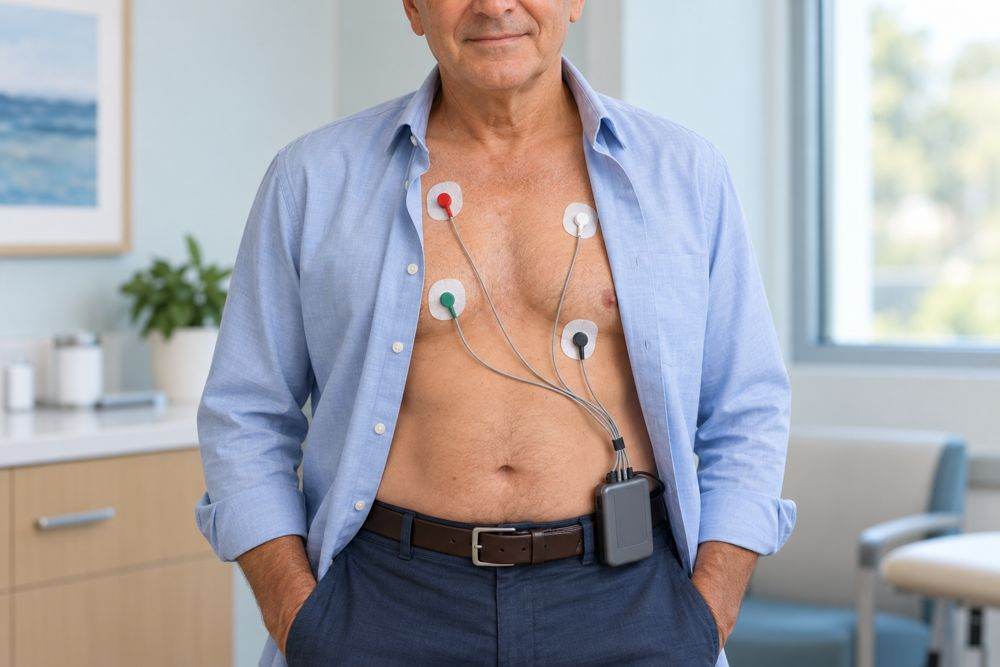
Match the monitor to symptom frequency and interpret symptom–rhythm correlation.
Match the recording window to the event
The goal is to correlate symptoms with rhythm or identify a clinically important arrhythmia. Choose a monitor long enough to have a realistic chance of capturing the event, with automatic detection when sudden loss of consciousness prevents activation.
Daily/frequent symptoms
Typical option: 24–48-hour Holter, or longer continuous recording
Practical point: Useful when an event is likely during recording.
Events within days/weeks
Typical option: Extended patch, external loop/event recorder, or mobile telemetry
Practical point: Duration and automatic detection/transmission vary; extended recording may last several weeks.
Infrequent recurrent unexplained syncope
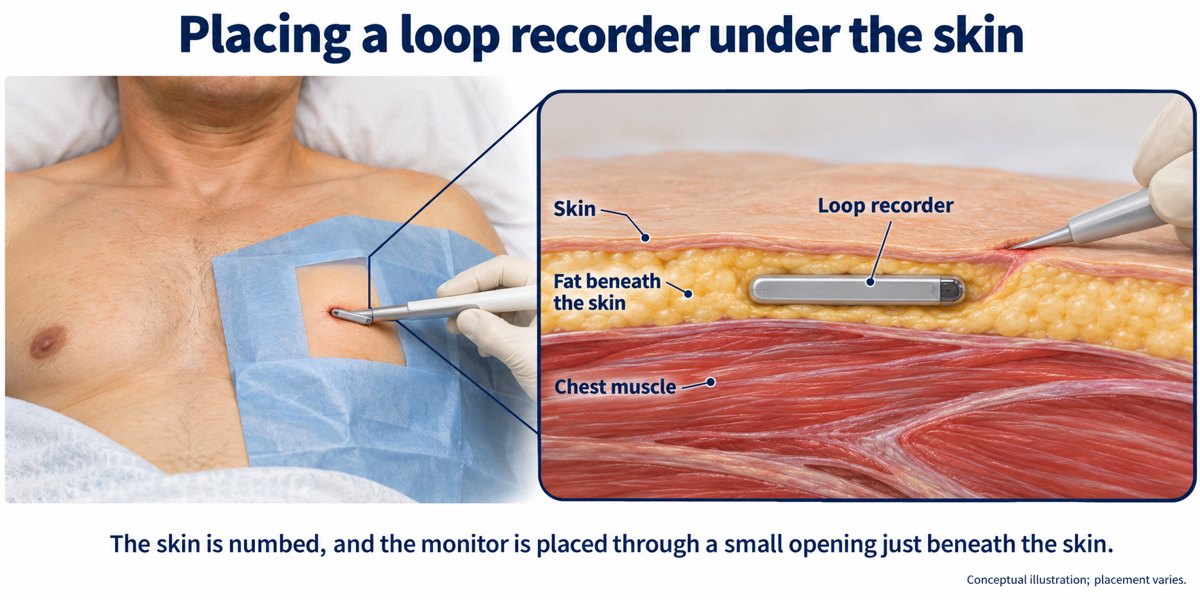
Typical option: Implantable loop recorder after appropriate assessment
Practical point: Long-term observation when a short external study is unlikely to capture an event.
High-risk or unstable presentation
Typical option: Urgent monitored evaluation
Practical point: Outpatient monitoring does not replace acute care.
An ILR is a small subcutaneous monitor that observes rhythm over a long period and stores automatically detected or patient-triggered events. Monitoring duration depends on the device.
Conceptual device illustration, not a calibrated size comparison. The recorder diagnoses rhythm; it does not provide pacing or shocks.Open full-size image →Illustrative subcutaneous placement. The implanting team determines the position and technique.Open full-size image →
Consider EP review for recurrent unexplained syncope after initial evaluation, particularly when an arrhythmia remains possible and symptoms are too infrequent for external recording.[7]
Make the monitor result interpretable
Teach the patient to use the event button when available and record the time, symptoms, activity, and position. Confirm wear instructions, connectivity, and who reviews the results.
A monitor without an event is often nondiagnostic. Symptoms captured with a normal rhythm make an arrhythmic explanation less likely for that episode. Incidental arrhythmias still require clinical interpretation; an automated alert alone is not the final diagnosis.[5], [6]
Remote monitoring is not an emergency response system.
Emergency symptoms require immediate medical care rather than waiting for a transmission to be reviewed.[8]
Connect the diagnosis to treatment
Documented symptomatic bradycardia or significant block may lead to pacing evaluation; dangerous ventricular arrhythmias require specialist treatment. Reflex and orthostatic mechanisms need their own treatment plans. Fainting alone does not establish a pacemaker indication.
Clinical takeaway: Establish the risk first, select a realistic recording window, and close the loop between symptoms, rhythm, and treatment.