Rhythm control interrupts the flutter. Rate control slows the ventricular response. Anticoagulation addresses stroke risk. Each has a different role.
RESTORE NORMAL RHYTHM
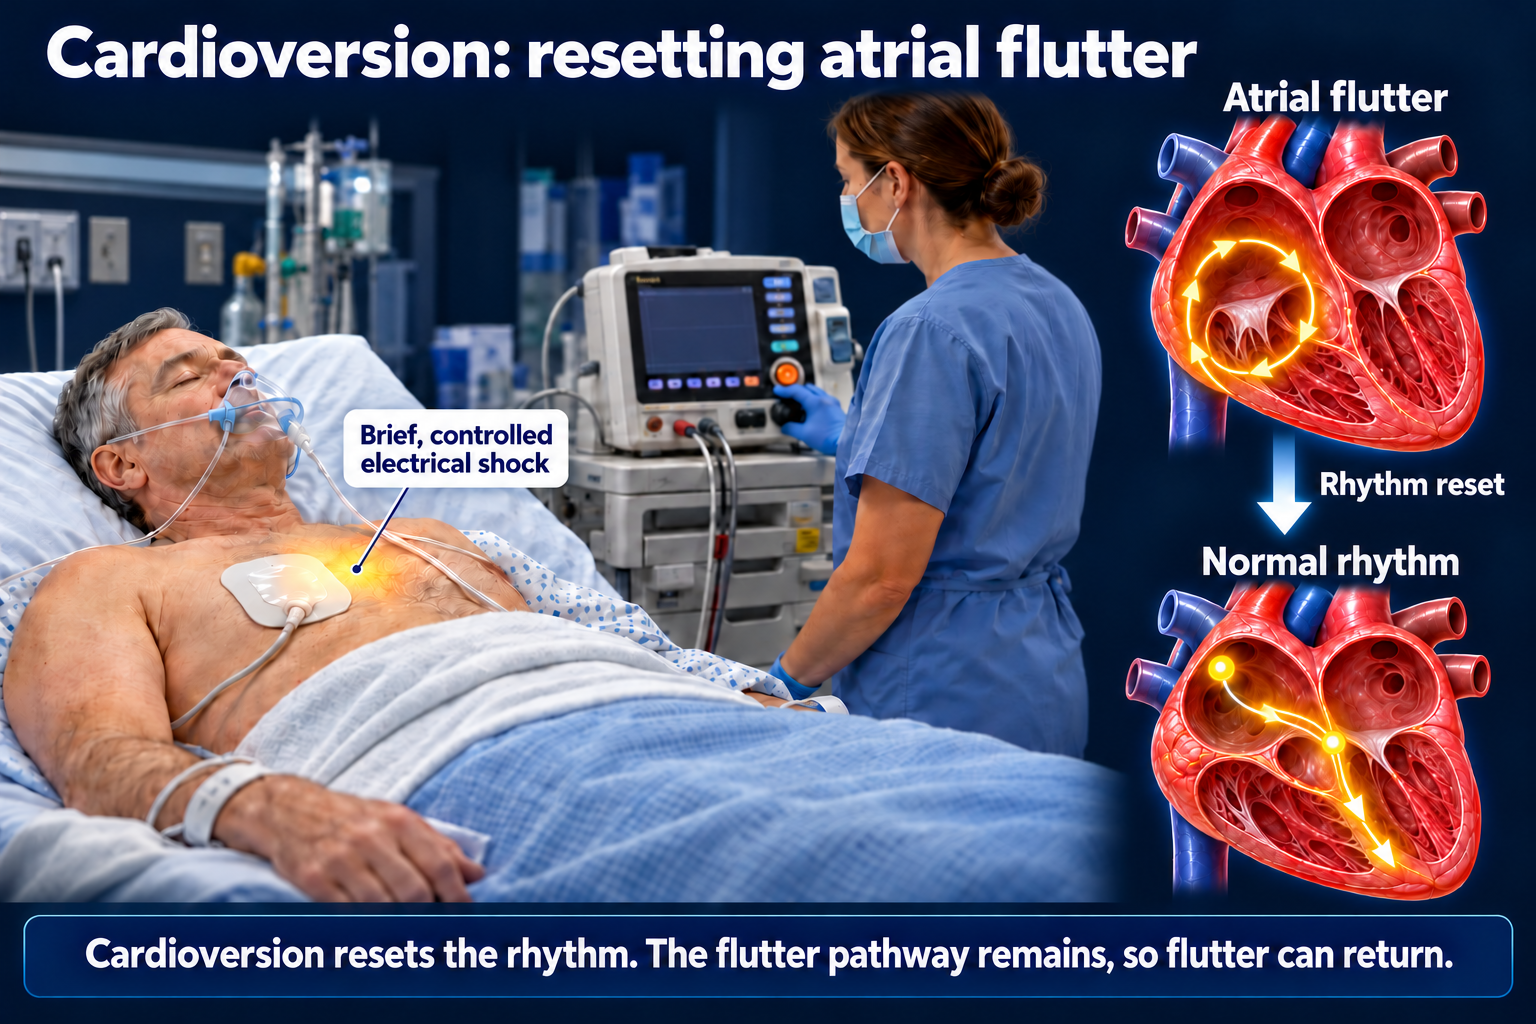
Cardioversion: reset the rhythm
Cardioversion resets the rhythm. The flutter pathway remains, so flutter can return.Open full-size image →
Electrical cardioversion can rapidly restore sinus rhythm.
However, cardioversion does not eliminate the pathway responsible for flutter. The rhythm may return because the circuit remains available.
For elective cardioversion, the treating team must address anticoagulation and possible atrial thrombus before proceeding.
INTERRUPT THE DEFINED CIRCUIT
Typical flutter ablation
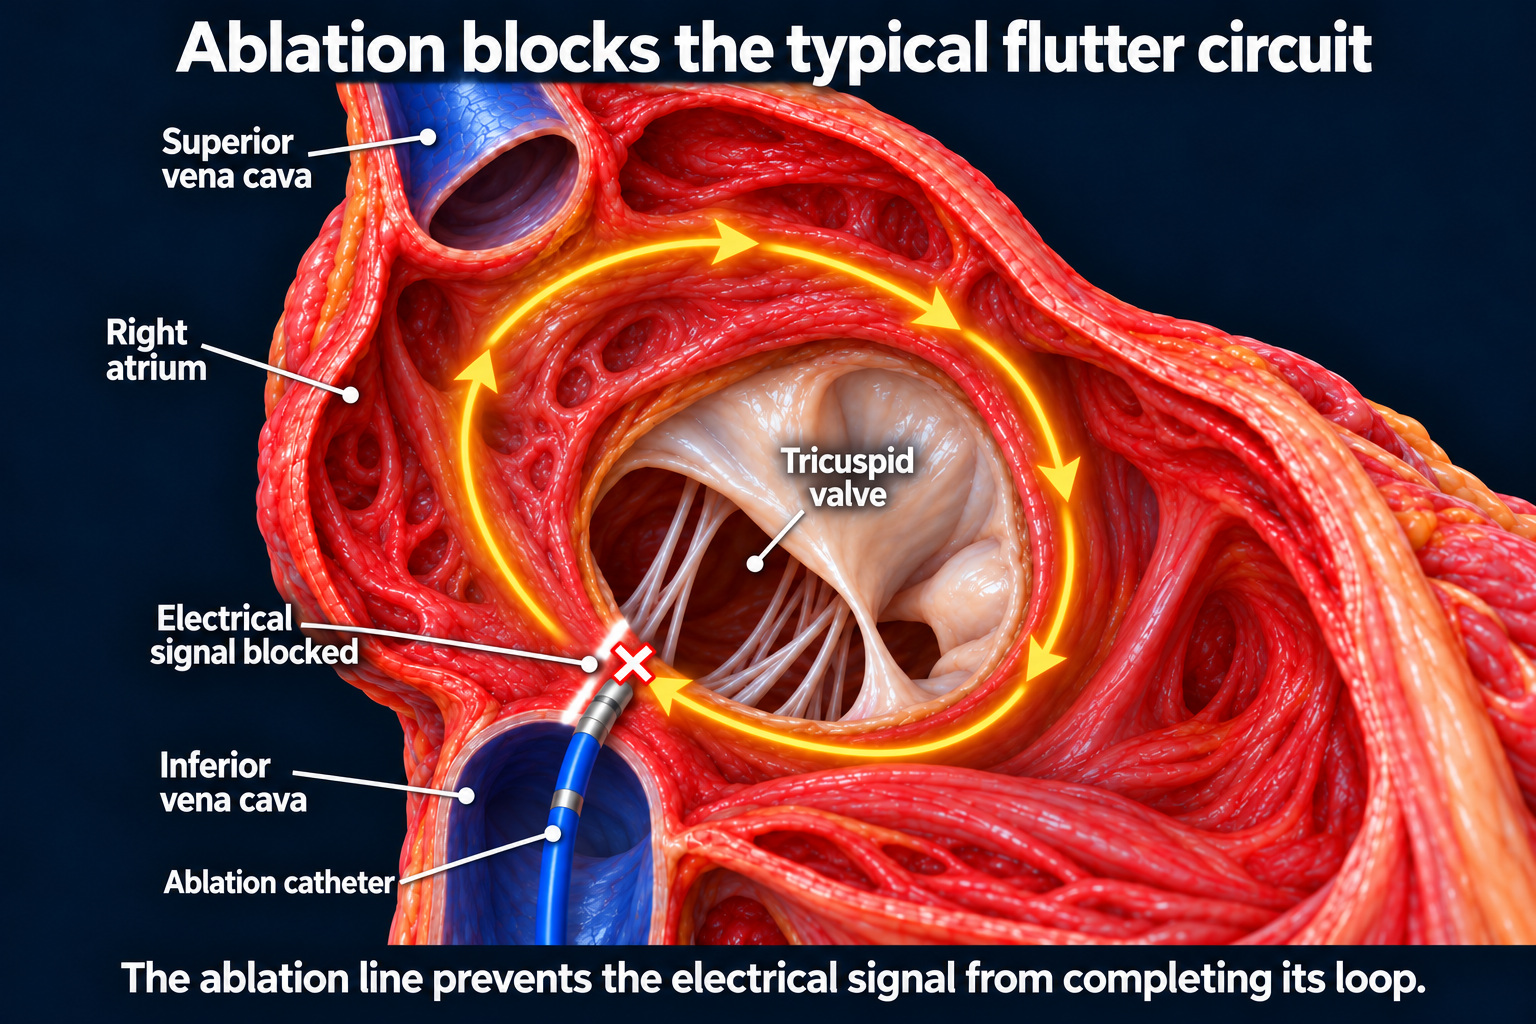
Ablation creates a line of block across the CTI, between the tricuspid annulus and inferior vena cava. Confirmed bidirectional block prevents conduction across the line in either direction.Open full-size image →
Typical flutter depends on conduction through the cavotricuspid isthmus (CTI) in the right atrium.
During ablation, the EP creates a line of conduction block across the CTI, between the tricuspid annulus and inferior vena cava. The goal is bidirectional block, preventing conduction across the line in either direction.
The racetrack analogy
The electrical signal is running around a racetrack. CTI ablation closes a critical section of the track so the signal can no longer complete the lap.
Typical flutter ablation offers a high likelihood of durable control of that circuit. It is an important option for symptomatic flutter or flutter that is difficult to rate-control—not something that must wait until multiple medications fail.
MAP THE CIRCUIT FIRST
Atypical flutter ablation
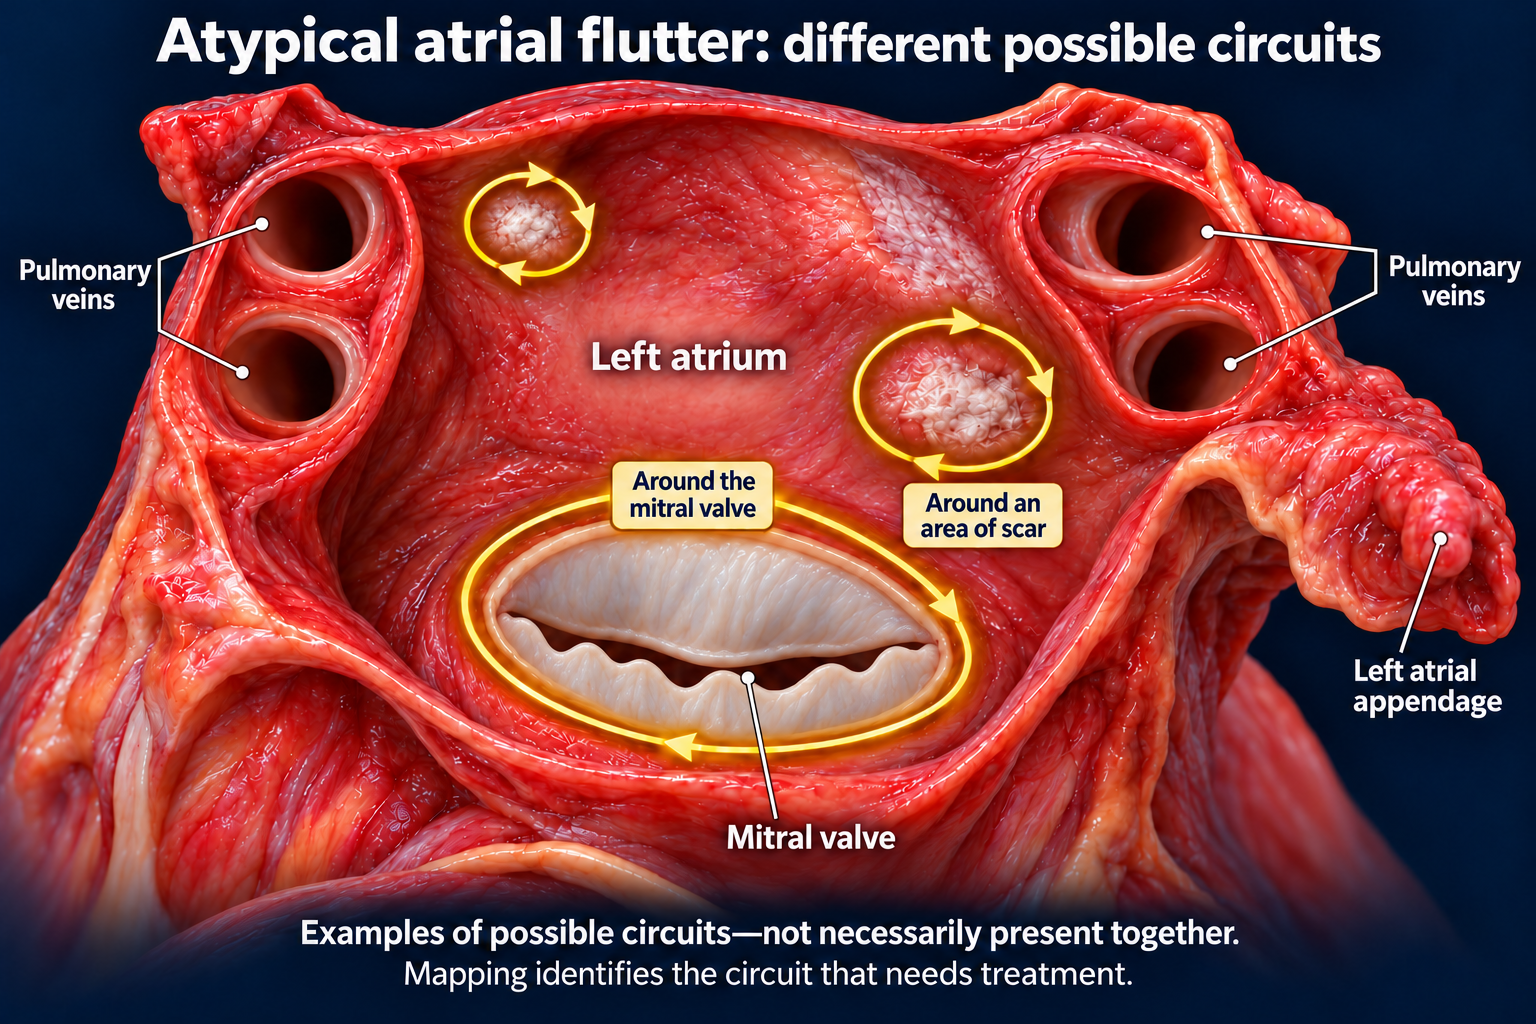
Mapping identifies the active circuit and its critical conduction pathway. These are alternative examples—not necessarily circuits occurring together. Atypical flutter can also arise in the right atrium.Open full-size image →
Atypical flutter does not depend on the CTI. Its circuit may travel around the mitral annulus, the left atrial roof, surgical scar, or previous ablation lines.
The EP uses three-dimensional mapping to identify the circuit and its critical conduction pathway.
A CTI line alone will not treat a flutter circuit that does not use the CTI. Treatment must match the mechanism.
Atypical flutter ablation is generally more complex. Outcomes depend on the circuit, underlying atrial disease, and prior procedures; recurrence or repeat treatment may occur.
MEDICATIONS HAVE DISTINCT ROLES
Where do medications fit?
Rate-control medications may reduce the ventricular rate while a rhythm strategy is arranged.
Antiarrhythmic medications may help restore or maintain sinus rhythm in selected patients. Their selection depends on ventricular function, coronary disease, kidney function, QT interval, interactions, and other factors.
For typical flutter, discuss ablation early rather than assuming indefinite medication escalation is the only option.
SET LONG-TERM EXPECTATIONS
Flutter ablation does not eliminate AFib risk
Successful CTI ablation treats the typical flutter circuit. It does not isolate pulmonary-vein triggers or eliminate the underlying tendency to develop AFib.
Patients may have AFib before flutter ablation or develop it afterward.
Patient-facing explanation
“We can treat this flutter circuit very effectively. You may still develop other atrial rhythms, including AFib, so follow-up remains important.”
CONTINUE FOLLOW-UP & STROKE PREVENTION
What happens after treatment?
After cardioversion or ablation:
Continue anticoagulation according to the procedural and long-term plan.
Reassess symptoms and rhythm recurrence.
Review whether rate-control or antiarrhythmic medications still serve a purpose.
Consider rhythm monitoring when clinically indicated.
Address contributing conditions such as hypertension, obesity, sleep apnea, and alcohol use.
Do not stop anticoagulation simply because the flutter was successfully ablated. The decision requires assessment of stroke risk, AFib history, and ongoing surveillance.
The referral message
Typical flutter: identify the circuit and discuss ablation early. Atypical flutter: refer for individualized mapping and treatment. Both: protect against stroke and maintain follow-up.